
Surgical release for adhesive capsulitis (frozen shoulder) is only the first phase of recovery. Ultimate clinical success depends entirely on strict adherence to a structured Post-Operative Guidelines Following Arthroscopic Capsular Release for frozen shoulder. Neglecting early mobilization can lead to recurrent capsular fibrosis, effectively neutralizing the surgical outcome.
Sleep Positioning and Comfort
During the first 4 weeks, patients must avoid sleeping directly on the operative shoulder to prevent mechanical stress on the healing joint capsule and avoid posterior humeral displacement.
- Optimal Position: Sleep on the contralateral (unaffected) side or supine (on your back) with a pillow supporting the operative arm.
- Pro-Tip: Utilizing a recliner or placing extra pillows to elevate the torso during the first two weeks can significantly reduce nocturnal discomfort and make sitting up easier.
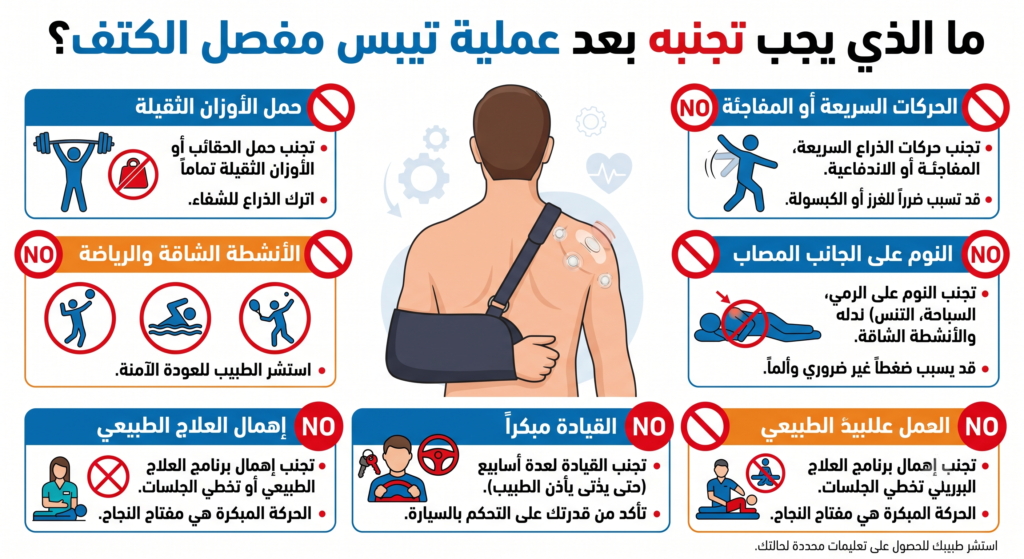
Key Contraindications Post-Operative Guidelines Following Arthroscopic Capsular Release for frozen shoulder (What to Avoid)
To protect the joint and ensure proper healing, avoid the following during the early recovery phases:
Lifting weights exceeding 1-2 kilograms during the first two weeks.
Sleeping on the affected shoulder during the first four weeks.
Wetting the wound or showering without a waterproof protective cover for at least the first week.
Stopping physical therapy sessions as soon as the pain improves — pain relief does not mean full recovery.
Driving a car before safely regaining rotational movement and grip strength.
Sudden overhead movements before the sixth week.
The Critical Role of Physical Therapy
Postoperative physical therapy must begin on Postoperative Day 1 or 2 to prevent the rapid reformation of intra-articular adhesions [1, 3].
- Phase I (Weeks 1–6): Focuses strictly on passive and active-assisted range of motion (ROM). Key exercises include pendulum swings, passive external rotation, and progressive forward flexion [1, 2].
- Phase II (Weeks 7–12): Transitions to active ROM, periscapular stabilization, and rotator cuff strengthening [2, 3].

Activity Resumption Timeline
| Activity | Expected Timeline |
| Light daily activities (eating, writing) | 1–2 weeks |
| Desk/Office work | 2–3 weeks |
| Driving | 3–4 weeks (pending surgeon clearance) |
| Light lifting | 6 weeks |
| Heavy manual labor & sports | 3–6 months |
Common Postoperative Pitfalls
- Premature PT Discontinuation: Patients often stop therapy around weeks 2–3 when initial surgical pain subsides. Stopping before achieving full functional ROM leads to chronic, recurrent stiffness.
- Misinterpreting the Week 6 Flare-up: A transient inflammatory response and mild loss of motion typically occur around week 6 [5]. This biological remodeling is normal and should not be mistaken for surgical failure; continuing therapy is essential.
- Neglecting Glycemic Control: Poor blood glucose management postoperatively can impair collagen synthesis and significantly prolong joint stiffness [5].
Red Flags: When to Contact Your Surgeon Immediately
Seek prompt medical evaluation if you experience any of the following:
- Signs of infection: Spreading redness, localized warmth, purulent discharge from incision sites, or a body temperature exceeding 38.5°C [4].
- Neurological symptoms: Persistent numbness, tingling, or sudden motor weakness in the hand or fingers [2].
- Sudden mechanical block: An abrupt, painful loss of joint mobility after documented progressive improvement [1].

Frequently Asked Questions: Recovery Following Arthroscopic Capsular Release
Why is immediate post-operative movement critical after arthroscopic capsular release?
Unlike reconstructive shoulder surgeries that necessitate tissue immobilization for healing, arthroscopic capsular release cuts away contracted fibrous tissue to restore volume to the glenohumeral capsule. If the shoulder remains still post-operatively, the body’s natural inflammatory cascade rapidly deposits new collagen bridges, leading to recurrent arthrofibrosis and loss of intraoperative range-of-motion gains.
How long should I wear the shoulder sling following capsular release?
The sling is strictly an accessory for initial comfort, not structural protection:
- First 24–48 Hours: Used while waiting for the regional interscalene nerve block to wear off and arm proprioception to return.
- Days 3 to 7: Discontinued for all indoor activities and only used optionally for protection in crowded public settings.
- Prolonged daytime sling use past the first week is discouraged to prevent stiffness.
How is postoperative pain managed to allow early physical therapy?
Adequate analgesia is required to tolerate the stretching exercises needed to keep the capsule open. A multimodal protocol is standard:
- Regional Nerve Block: Provides profound numbness and pain relief for the initial 12 to 24 hours.
- Scheduled NSAIDs & Acetaminophen: Mitigates inflammatory capsular cytokines and soft-tissue swelling.
- Oral Narcotics: Taken as a short-term rescue agent 30 to 45 minutes prior to therapy sessions during the first 1 to 2 weeks.
- Cryotherapy: Ice machine or cold packs applied for 15–20 minutes after completing home stretches.
When should formal outpatient physical therapy begin?
Formal supervised physical therapy should begin between postoperative day 1 and 5. Early appointments focus on passive end-range stretching, joint mobilizations, and therapist-assisted stretches. This is complemented by an aggressive home exercise program performed 3 to 5 times daily in 10-to-15-minute intervals.
What are the earliest home exercises to perform right after surgery?
Starting on postoperative day 1, key early exercises include:
- Codman Pendulum Swings: Bending at the waist and letting gravity swing the arm in gentle clockwise, counterclockwise, and forward-back circles.
- Supine Passive Forward Elevation: Lying on your back and using the opposite arm or a light dowel to lift the operative arm overhead.
- External Rotation with Cane/Wand: Lying supine with elbows tucked at 90°, gently pushing the operative hand outward.
- Distal Muscle Pumps: Squeezing a stress ball and flexing/extending the wrist and elbow to maintain lymphatic circulation.
How should the arthroscopic incision portals be cared for at home?
The arthroscopy portal sites require clean, dry conditions for the first 48 to 72 hours. Showers may be taken after 48 to 72 hours by covering portals with waterproof bandages. Do not scrub the incision areas; pat them dry and replace with clean, breathable dressings. Full immersion in bathtubs, swimming pools, or hot tubs is prohibited until the surgical sutures or staples are removed at the two-week follow-up visit.
What sleeping positions are best during recovery from capsular release?
Lying flat in bed often aggravates nocturnal capsular tension and posterior joint irritation. Sleeping in a semi-reclined position (at a 30° to 45° angle) using a recliner chair or bed wedge pillow is recommended for the first 2 to 4 weeks. Placing a pillow underneath the elbow and forearm of the operated arm keeps the humerus forward, preventing extension strain on the healing anterior capsule.
How does diabetes mellitus impact post-operative recovery?
Diabetic patients have a higher baseline risk of refractory adhesive capsulitis due to advanced glycation end-products (AGEs) cross-linking collagen fibers. During recovery, tight blood glucose management is critical to suppress excessive tissue proliferation. Diabetic patients also require a more persistent, extended course of physical therapy to retain terminal motion gains compared to non-diabetic peers.
When can I safely return to driving and work activities?
Functional milestones guide return to activity:
- Driving: Permitted once narcotic medications have ceased completely and you have normal steering control (typically 1 to 2 weeks).
- Desk & Computer Work: Can often be resumed within 5 to 7 days, provided the arm is supported and stretching breaks are taken every hour.
- Manual Labor & Overhead Work: Requires progressive rotator cuff and periscapular strengthening, typically clearing at 8 to 12 weeks post-surgery.
What red-flag warning signs require immediate surgical contact?
Contact your surgical team or proceed to urgent care if you experience:
- A fever exceeding 38°C (100.4°F) or persistent chills.
- Spreading redness, warmth, or purulent fluid discharge from the portal incisions.
- Sudden, severe pain that does not respond to prescribed analgesics.
- Persistent tingling, numbness, or loss of motor function in the hand and fingers extending beyond the expected duration of the nerve block.
- Shortness of breath, chest pain, or asymmetric swelling in the calf (to rule out deep vein thrombosis).
Medical References
- Post-Operative Rehabilitation Protocol: Arthroscopic Glenohumeral Capsular Release — Twin Cities Orthopedics (3-Phase Protocol)
- Arthroscopic Capsular Release for Frozen Shoulder — Post-Op Rehabilitation Protocol, Illinois Bone & Joint Institute
- Shoulder Arthroscopic Capsular Release Rehabilitation Protocol — OrthoArizona (Phase I–III)
- Shoulder Arthroscopic Capsular Release Rehabilitation — Hospital for Special Surgery (HSS)
- Frozen Shoulder Release: Post-Op Protocol — Southampton Shoulder Clinics
- Rehabilitation Guide Following MUA and Arthroscopic Capsular Release — Robert Jones & Agnes Hunt NHS Trust (2024)
- Post-Op Arthroscopic Releases for Adhesive Capsulitis — Atlantic Medical Group Orthopedics
- Outpatient Post-Operative Physiotherapy Guidelines: Distension, MUA & Arthroscopic Capsular Release — Oxford University Hospitals NHS