
complications of shoulder arthroplasty are relatively rare. Serious complications are uncommon, and surgeon experience helps reduce them. Despite potential risks, patient satisfaction reaches 90%.
Complication Incidence Table
| Complication | Incidence Rate | High-Risk Groups |
| Joint Stiffness | 2–5% | Poor physical therapy adherence |
| Superficial Infection | 0.5–1% | Diabetic/Obese patients |
| Deep Infection | 0.3–1% | Immunocompromised patients |
| Periprosthetic Fracture | 0.6–2.4% | Osteoporosis, falls |
| Instability/Dislocation | 2–4% (Reverse) | Component malpositioning |
| Polyethylene Wear | 1–3% (>10 yrs) | Excessive physical activity |
| Nerve Injury | <1% | Intraoperative stretch |
| Revision Surgery | 5–10% (10 yrs) | Implant quality, compliance |
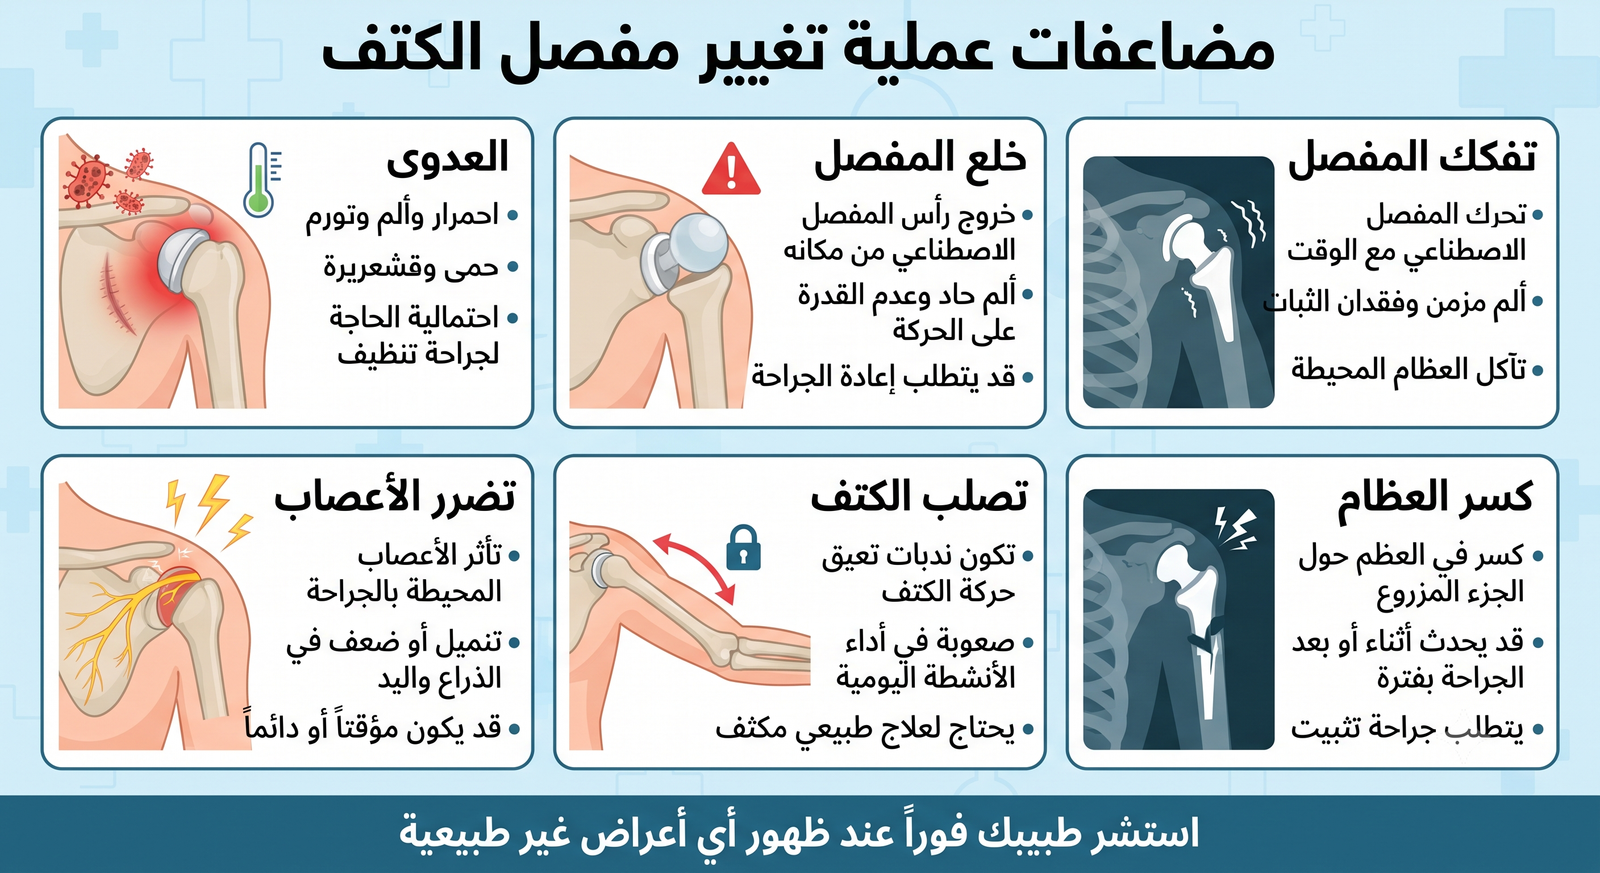
Clinical Course: Early vs. Late Complications
- Early Complications (Weeks): Post-operative pain and swelling are expected; however, pain unresponsive to analgesics requires immediate evaluation. Wound infections present as redness, heat, or discharge. Transient nerve injury (numbness/weakness) is rare (<1%) and typically resolves within weeks.
- Late Complications (Months/Years): Polyethylene wear or component loosening can occur after a decade, leading to recurrent pain. Periprosthetic fractures are often related to falls or underlying osteoporosis.
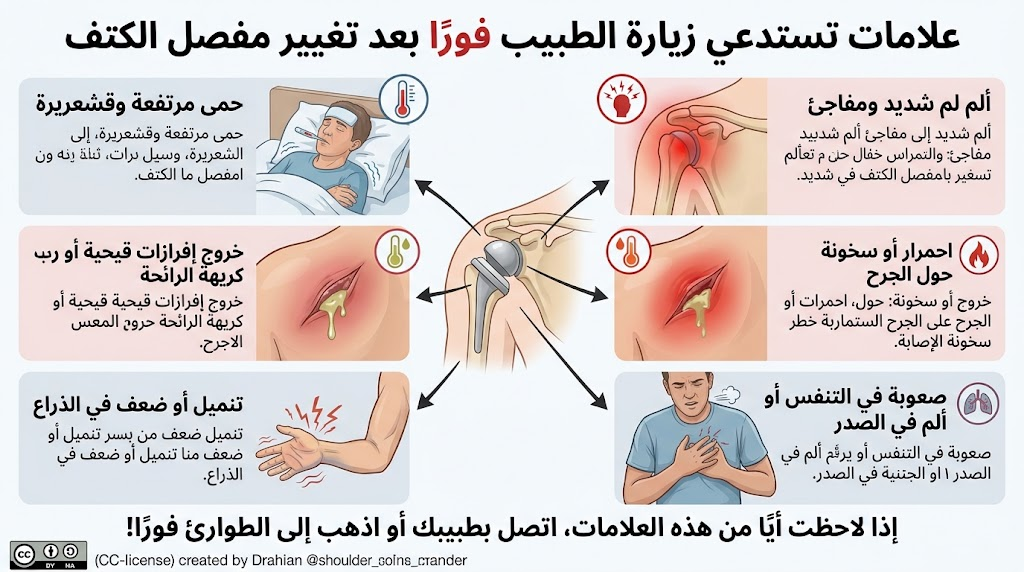
Warning Signs Requiring Urgent Medical Attention:
- Fever >38.5°C after the third post-operative day.
- Sudden, severe shoulder pain.
- Increased swelling or redness around the incision.
- New “popping” or clicking sounds accompanied by pain.
- Return of pain after a period of improvement.
Mitigation Strategies
Most complications are preventable. Selecting an experienced shoulder surgeon helps reduce complication rates. Pre-operative optimization—specifically managing diabetes and smoking cessation at least 6 weeks prior—is essential to reduce infection risk and promote wound healing.
| Controllable Factor | Impact |
| Specialist Surgeon | Fewer complications |
| Diabetes Management | Significant reduction in infection |
| Smoking Cessation | Improved wound healing |
| Physical Therapy | Prevention of primary stiffness |
| Weight Restriction (<5kg) | Reduced wear and loosening |
Rehabilitation and Outcomes
Physical therapy (PT) is the primary defense against joint stiffness.
Standard Rehabilitation Protocol:
- Protection (Weeks 1–6): Sling usage, elbow/hand exercises, cryotherapy.
- Passive Motion (Weeks 6–12): Gradual mobilization assisted by a therapist.
- Early Strengthening (Months 3–6): Light resistance exercises.
- Advanced Strengthening (Months 6–12): Return to permitted activities.
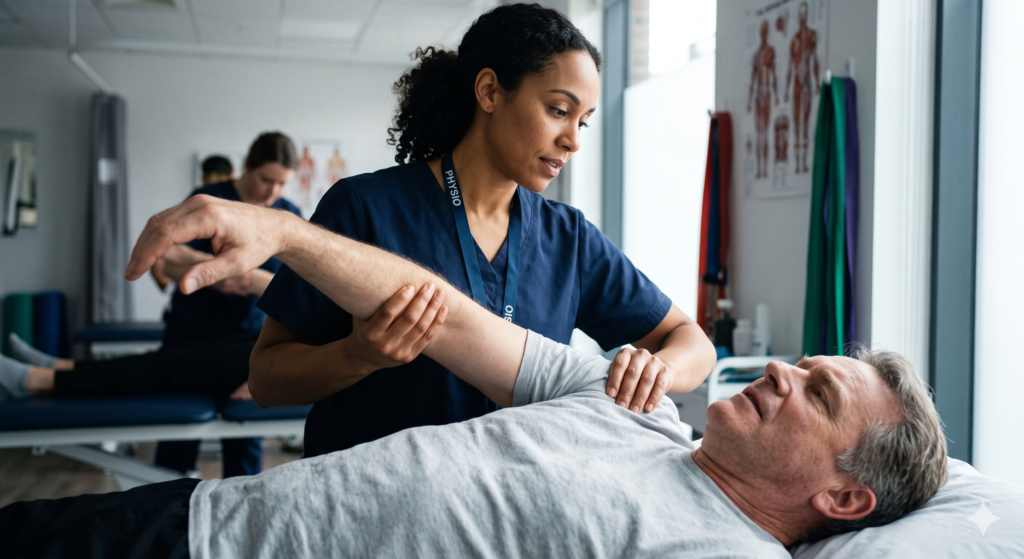
Functional Recovery:
Patients typically achieve maximum improvement between 12 and 18 months post-surgery. Success is reflected in the SANE score, which improves from 31% pre-operatively to 73% of normal function. Long-term functional success requires permanent avoidance of lifting heavy weights (>5–7 kg) and high-impact contact sports.

Success Rates
Prosthesis survival rates are excellent, with 90% at 10 years and 80% at 20 years. Modern implant generations show improved longevity over previous designs. With proper surgical selection and patient compliance, shoulder arthroplasty remains one of the most successful orthopedic procedures for improving quality of life.
frequently asked questions
Frequently Asked Questions: Complications & Recovery
refernces
https://www.hss.edu/health-library/conditions-and-treatments/list/shoulder-replacement-surgery
(Hospital for Special Surgery — instability, rotator cuff tear, infection, nerve damage, glenoid loosening, stiffness)
https://my.clevelandclinic.org/health/treatments/8290-shoulder-replacement
(Cleveland Clinic — blood clots, fractures, infection, nerve damage, prosthetic loosening/dislocation)
https://www.arthritis-health.com/surgery/shoulder-surgery/total-shoulder-replacement-risks-and-complications
(Arthritis-Health — rotator cuff damage, prosthetic misalignment, bone fracture, joint dislocation)
https://pmc.ncbi.nlm.nih.gov/articles/PMC9246563
(Medical complications after shoulder arthroplasty — overall MC rate 12%, cardiovascular, renal, respiratory — full review)
https://pmc.ncbi.nlm.nih.gov/articles/PMC12277745/
(Complication rates in patients ≤45 years — TSA 29% overall complication rate — infection, glenoid loosening, cuff tear)
https://pmc.ncbi.nlm.nih.gov/articles/PMC12372930/
(Knowledge mapping of postoperative complications — infection, calcification, instability, osteoarthritis — 2025)
https://pmc.ncbi.nlm.nih.gov/articles/PMC12514742/
(Elective shoulder arthroplasty outcomes — readmission rates, LOS, complications — 2025)
https://pmc.ncbi.nlm.nih.gov/articles/PMC13407823/
(Arthroscopy for painful shoulder arthroplasty — glenoid loosening, cuff failure, infection — 2026)
https://pubmed.ncbi.nlm.nih.gov/32146041/
(Cost analysis — 90-day complication rate 2.3%, reoperation 0.6%, readmission 1.8%)
https://doaj.org/article/87cb83eaed4347b0bda1cc7e253b1aeb
(JSES International — complications in reverse vs anatomic arthroplasty — 2025)