
Surgical stabilization for recurrent shoulder dislocation achieves excellent outcomes in most cases. However, overlooking potential complications leaves patients making uninformed choices and delays necessary assistance when signs of deviation from the normal recovery path appear. This article details the Complications of Shoulder Dislocation Surgery associated with shoulder dislocation surgery.
What Are the Complications of Shoulder Dislocation Surgery?
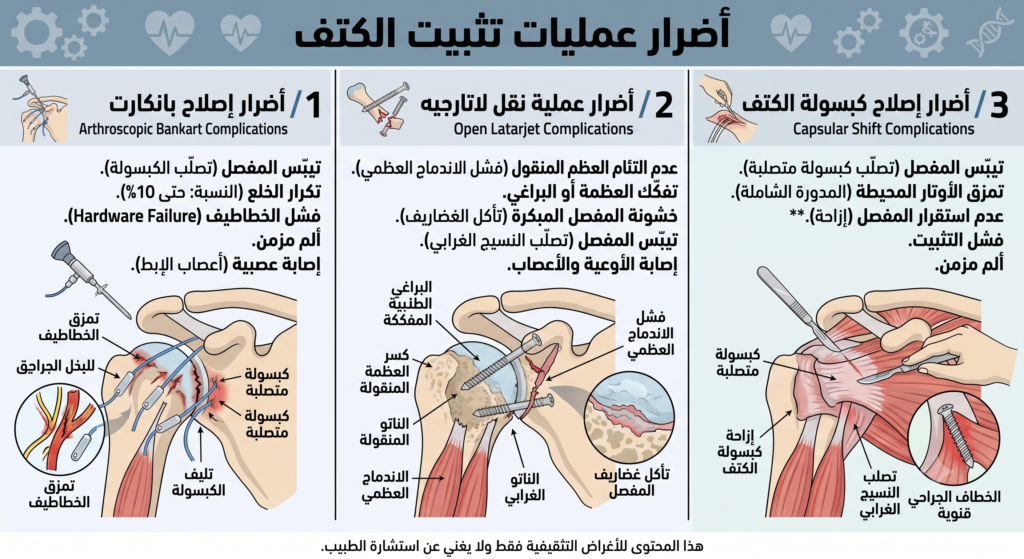
Complications of shoulder dislocation surgery fall into two categories: general complications shared by all shoulder surgeries—such as infection, stiffness, and bleeding (each occurring in less than 1% of cases)—and specific complications native to the type of procedure. A Bankart repair carries a long-term recurrent dislocation risk of about 16%, while the Latarjet procedure carries a hardware/screw complication risk ranging from 0% to 16%.
Re-operation after general arthroscopic shoulder surgery is uncommon. However, procedures addressing shoulder instability carry a relatively higher rate linked directly to recurrent dislocations rather than a failure of the surgical technique itself. Understanding this distinction is crucial; technical surgical success does not eliminate the possibility of a future dislocation if the patient returns to collision sports prematurely. Complications are also categorized timeline-wise into early complications (occurring within the first few weeks) and late complications (such as osteoarthritis or recurrent instability).
Complications of the Arthroscopic Bankart Procedure
The primary complication of an arthroscopic Bankart repair is a recurrent dislocation, which is about 16% at 10 or more years. This risk is noticeably elevated in patients under the age of 20 and collision athletes. Temporary postoperative stiffness can occur.
- Recurrent Dislocation: About 16% at 10+ years (31% for any recurrent instability).
- Post-operative Stiffness: Can occur after shoulder surgery and responds well to physical therapy.
- Anchor Fixation Failure: Rare, but requires revision surgery.
- Peripheral Nerve Damage (Axillary Nerve): Extremely rare and mostly temporary.
- Infection: Less than 1% in arthroscopic cases.
- Residual Pain: Responds to intra-articular injections in a small percentage of patients.
Complications of the Latarjet Procedure
Latarjet complications are more diverse than Bankart complications due to the technical complexity of the procedure. They include hardware/screw complications (0% to 16%), non-union of the bone graft (5% to 8%), and long-term osteoarthritis (8% to 42% at a 5-year follow-up). Notably, the recurrent dislocation rate itself is only 1% to 5%, which is the lowest among all stabilization techniques.
- Screw Complications (Migration, Fracture, Irritation): 0% to 16%, occasionally requiring screw removal.
- Coracoid Non-union: 5% to 8%, which can potentially impact long-term stability.
- Degenerative Joint Osteoarthritis: Appears in 8% to 42% of cases at a 5-year follow-up according to systematic reviews.
- Recurrent Dislocation: Only 1% to 5%—the lowest rate among all stabilization procedures.
- Neurovascular Damage: Extremely rare and primarily associated with the surgeon’s learning curve.
- External Rotation Stiffness: A mild loss of external rotation in some patients.
Differences Between Bankart and Latarjet Complications
| Complication | Arthroscopic Bankart | Latarjet |
| Recurrent Dislocation (5 Years) | About 16% at 10+ years | 1% – 5% |
| Post-operative Stiffness | 10% | Less common |
| Hardware/Device Complications | Rare (Suture Anchors) | 0% – 16% (Screws) |
| Long-term Joint Osteoarthritis | Lower | 8% – 42% at 5 years |
| Bone Non-union | Not Applicable | 5% – 8% |
| Nerve Injury Risk | Rare | Rare, but relatively higher |
Factors That Increase the Risk of Complications
Five documented factors elevate the risk of complications after shoulder stabilization: an age under 20, participation in collision sports, choosing an inappropriate procedure for the degree of bone loss, the surgeon’s experience specifically with the Latarjet technique, and a premature return to collision activities before the surgeon’s 4-month evaluation.
An age under 20 at the time of surgery is statistically linked to a high recurrence rate after a Bankart repair. This demographic is highly prevalent in Egypt among football players, wrestlers, and martial artists. A key error to avoid is performing a Bankart repair on a patient who needs a Latarjet because of significant bone loss. This clinical mismatch sharply drives up recurrence and exposes the patient to a far more complex revision surgery. Bone loss is best measured with 3D CT, as MRI can underestimate it. Instead, a high-resolution 3D CT scan is mandatory for accurate surgical planning. A surgeon who does not routinely order a CT scan before deciding between a Bankart or a Latarjet may misclassify the pathology.
When Do Symptoms Indicate a Post-Operative Complication?
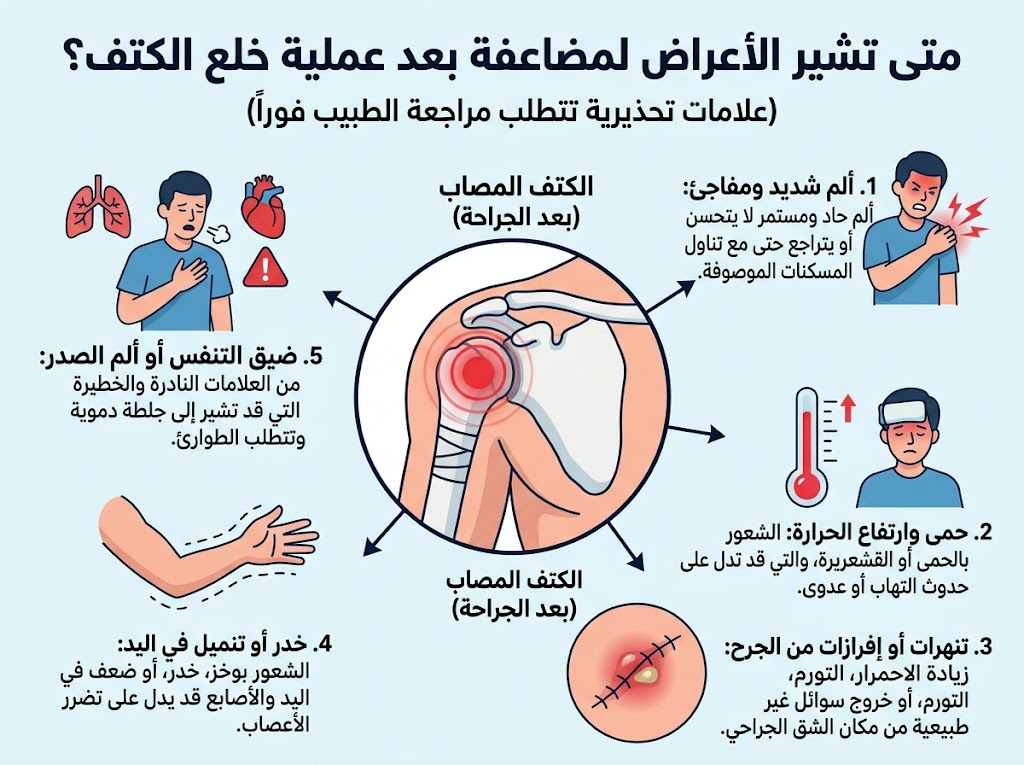
Patients must contact their surgeon immediately if any of the following warning signs develop:
- Redness, warmth, or drainage from the incision: Indicates a potential infection requiring immediate evaluation.
- A fever exceeding 38.5°C after the third post-operative day: Warrants emergency laboratory blood tests.
- Persistent numbness or weakness in the fingers or hand: Demands an immediate neurological assessment.
- Sudden, severe pain unrelated to physical therapy exercises: Necessary to rule out an intra-articular issue or screw fracture.
- A sensation of shoulder instability after the sixth week: Requires urgent radiological evaluation.
How to Prevent Complications After Shoulder Dislocation Surgery
Preventing complications begins pre-operatively with an accurate diagnosis of bone stock to choose the appropriate procedure, and continues post-operatively through absolute compliance with physical therapy and avoiding contact sports until cleared at the 4-to-5-month surgical evaluation.
- Obtain a pre-operative 3D CT scan to quantify bone loss precisely.
- Choose a Latarjet procedure over a Bankart repair if glenoid bone loss exceeds 20%.
- Ensure the surgeon has performed an adequate volume of Latarjet procedures, as the learning curve directly impacts safety.
- Begin structured physical therapy on the first or second post-operative day rather than waiting a week.
- Do not return to contact or collision sports prior to a direct 4-to-5-month clinical evaluation by your surgeon.

Shoulder Stabilization Complications FAQ
Clinical statistics, comparative risks, and preventative guidelines regarding complications after shoulder dislocation surgery.
General surgical risks common to all shoulder operations, such as infection, severe bleeding, and joint stiffness, are exceptionally low, occurring in less than 1% of cases per complication. However, total complication rates vary noticeably depending on the technique chosen:
- Arthroscopic Bankart Repair: Carries a total specialized complication rate of under 5%.
- Open Latarjet Procedure: Carries a higher complication rate ranging from about 30% (mostly minor), reflecting its structural complexity.
The failure or re-dislocation rate after a Bankart repair changes dramatically depending on follow-up duration and candidate selection:
- Short-term (<5 years): Maintains a low recurrence rate of 6.7% in carefully selected patients who lack critical bone stock loss.
- Long-term (10+ years): Recurrence rates rise significantly up to 20.9% over a mean 13.8-year follow-up. This long-term failure is heavily linked to patients with unrecognized bone loss who should have originally received a Latarjet procedure.
Because the Latarjet technique involves shifting bone and hardware fixation, its complication profile is highly unique:
- Hardware/Screw Complications: Loosening, screw fracturing, or local tissue irritation occurs in 0% to 16% of cases, sometimes requiring secondary hardware removal.
- Coracoid Non-union: The transferred bone graft fails to fuse with the scapular glenoid rim in 5% to 8% of patients, which can compromise long-term joint stability.
- Degenerative Osteoarthritis: Long-term follow-ups show radiographic signs of arthritis in 8% to 42% of patients at 5 years, largely initiated by the trauma of original dislocations.
The Latarjet procedure provides the highest structural stability, limiting recurrent dislocations to just 1% to 5%—the lowest recurrence rate among all stabilization choices.
By contrast, an arthroscopic Bankart repair exhibits a higher overall failure and re-dislocation profile, stretching from about 16% at 10+ years depending on the time elapsed from surgery and pre-existing patient anatomy.
American Knee & Shoulder Center DataAn age under 20 years old at the time of surgery is the single strongest statistically documented risk factor for a recurrent dislocation following an arthroscopic Bankart repair.
This high-risk demographic represents a massive clinical subset among young competitive collision athletes (such as football players, wrestlers, and mixed martial artists) who frequently exhibit high soft-tissue elasticity and substantial re-injury forces.
Source: Clinical Failure Timeline StudiesThe most frequent error in modern surgical planning is executing a soft-tissue Bankart repair on a joint that possesses glenoid bone loss exceeding 20%. This structural mismatch sharply drives up recurrence rates and exposes the patient to a highly complex revision surgery later.
Crucial Fact: Relying solely on an MRI can lead to this error, because standard MRI scans underestimate the true volume of bone loss in some cases. A high-resolution 3D CT scan is mandatory before the operation to avoid misclassification.
Source: International Shoulder Surgical LiteratureIn roughly 10% of shoulder operations, temporary joint stiffness and restricted mobility are observed during the early post-operative weeks. This is a normal physiological healing trait that typically resolves entirely within 3 months of a structured physical therapy protocol.
For the Latarjet procedure specifically, patients should expect a minor, permanent mild loss of external rotation compared to pre-injury levels, which is a known trade-off for the procedure’s high stability.
Source: Post-Operative Mobility StatisticsNo, peripheral nerve injuries (most commonly impacting the axillary nerve) are extremely rare. In the vast majority of cases, any neurovascular symptoms are completely transient and stem from temporary tissue traction or stretching during surgical maneuvers rather than structural nerve transection.
Because the deep neurovascular pathways of the shoulder are highly intricate, avoiding this complication is directly related to the surgeon’s specialized learning curve and volume of operations.
Source: ShoulderDoc Neurovascular Risk ReportsPatients must closely monitor their recovery and contact their surgical team immediately if any of the following warning signs manifest:
- Redness, localized warmth, or fluid drainage: Suggests an acute wound infection that requires immediate diagnostic assessment.
- A fever exceeding 38.5°C after day 3: Demands emergency laboratory blood profiles.
- Persistent numbness or sudden weakness in the hand/fingers: Warrants immediate neurological screening.
- Sudden, sharp pain at rest: Requires evaluation to rule out an intra-articular tissue failure or screw fracture.
- A sensation of instability or catching after week 6: Demands urgent radiological re-evaluation.
Minimizing surgical risks is achieved through five specific clinical actions:
- Insist on a high-resolution 3D CT scan prior to surgical planning to map out exact bone stock.
- Opt for a Latarjet procedure over a Bankart repair if glenoid bone loss is quantified at 20% or more.
- Verify that your orthopaedic surgeon routinely performs a high annual volume of Latarjet stabilizer surgeries.
- Begin structured, specialized physical therapy exercises on post-operative day 1 or 2 rather than delaying rehabilitation.
- Strictly avoid all contact sports or heavy lifting until undergoing a direct, formal clinical evaluation by your surgeon at the 4-to-5-month mark.
References
- Long-Term Outcomes of Bankart and Latarjet Repairs Including Complications: Systematic Review — Open Access Journal of Sports Medicine (2017)
- Complications of the Latarjet Procedure: Graft Osteolysis, Arthritis, Neuropraxia, Nonunion — PMC
- Complications Related to Latarjet Shoulder Stabilization: A Systematic Review — Am J Sports Med (2023)
- Complications and Re-Operations After Bristow-Latarjet Shoulder Stabilization: Systematic Review — J Shoulder Elbow Surg (2013)
- Primary Latarjet Procedure: Graft Resorption, Degenerative Changes & Complications at Minimum 2-Year Follow-Up — Systematic Review (2023)
- Primary Latarjet vs. Latarjet After Failed Bankart Repair — Complication & Revision Rates: Systematic Review — J ISAKOS (2023)
- Complications in Shoulder Arthroscopy: Prevention, Management & Surgical Techniques (2026)