
A comprehensive medical guide by Prof. Dr. Ibrahim Abdelmonem, Professor of Orthopedic Surgery at Ain Shams University: Causes and symptoms of shoulder joint inflammation, the difference between it and tendon tears, and when you need surgery.
What is shoulder joint inflammation?
Shoulder joint inflammation is the deterioration of the articular cartilage lining the glenohumeral joint or inflammation of the surrounding tissues, causing chronic pain and progressive stiffness that limits daily activity. It mainly affects those over the age of fifty, and its rates increase among workers engaged in repetitive manual labor or those with an underlying rheumatic disease.
The shoulder joint consists of three joints: the glenohumeral joint (most affected in arthritic inflammation), the acromioclavicular joint (AC joint), and the sternoclavicular joint. The articular cartilage does not contain blood vessels, which makes its recovery slow and causes frequent inflammation to accumulate without noticeable pain in its early stages.
Causes of Shoulder Joint Inflammation
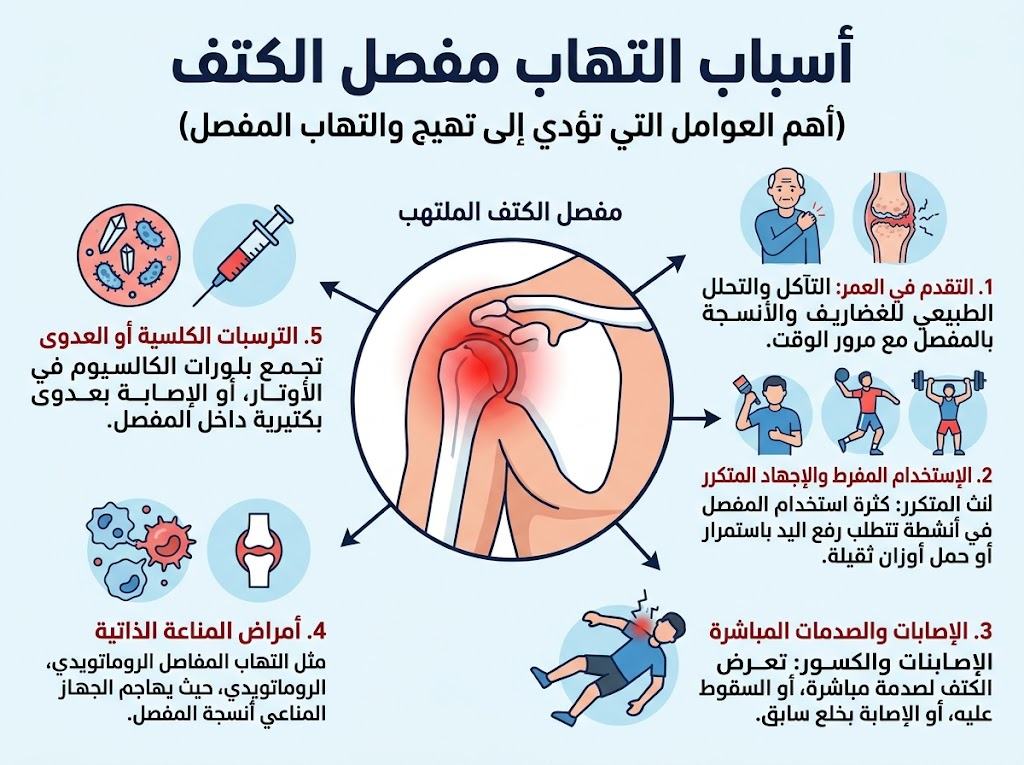
Shoulder joint inflammation is not a single diagnosis, but an umbrella comprising five distinct types, each with a different mechanism and treatment plan.
| Type of Inflammation | Mechanism | Most Affected Category |
| Osteoarthritis | Progressive cartilage wear and tear due to use and age | Over 55 years |
| Rheumatoid Arthritis (RA) | An autoimmune attack on the synovial membrane | Women aged 30–60 (at a ratio of 2–3:1 compared to men) |
| Adhesive Capsulitis (Frozen Shoulder) | Thickening of the capsular connective tissue after prolonged immobilization | Diabetics (at double the risk compared to others) |
| Calcific Tendinitis of the Rotator Cuff | Calcium carbonate deposition inside the supraspinatus tendons | Ages 30–60, more common in computer users |
| Post-traumatic Inflammation | Cartilage damage following an old shoulder fracture or dislocation | Any age group with a history of injury |
Additional Clinically Proven Risk Factors: Long-term high-dose corticosteroid use, smoking, alcohol abuse (associated with non-traumatic osteonecrosis), and sickle cell anemia (relatively common in Egypt).
Symptoms of Shoulder Joint Inflammation
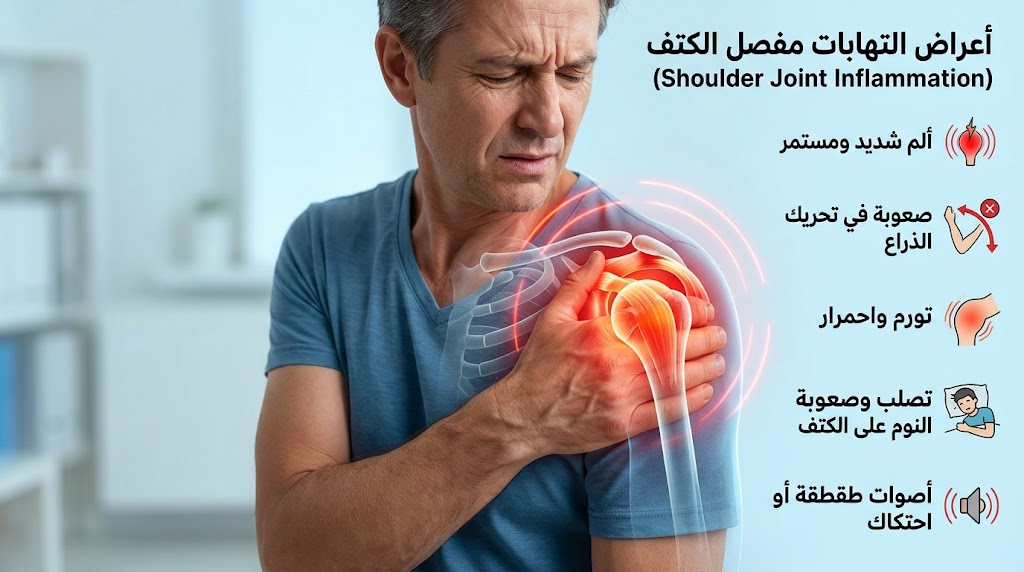
The four defining symptoms of shoulder joint inflammation: deep pain in the back of the shoulder that worsens with weather changes, morning stiffness lasting more than 30 minutes, a grinding sound (crepitus) with movement, and night pain that prevents sleeping on the affected side.
| Symptom | Clinical Detail | Risk Indicator |
| Deep posterior pain | Concentrated in the posterior region of the shoulder; indicates glenohumeral joint involvement | No |
| Top of shoulder pain radiating to the neck | Indicates AC joint involvement | No |
| Stiffness lasting > 30 minutes in the morning | Sign of an immune (rheumatic) rather than degenerative inflammation | Yes — requires a rheumatology evaluation |
| Crepitus (palpable grinding sound) | Evidence of cartilage loss | No |
| Complete loss of passive range of motion | Distinguishes frozen shoulder from tendon tears | Yes — see your doctor immediately |
| Swelling, localized heat, and redness | Indicates septic arthritis | Yes — surgical emergency |
| Marked weakness in lifting the arm forward | Strongly suggests a supraspinatus tendon tear | Yes |
Night pain that wakes the patient from sleep is classified among the quality-of-life-impairing symptoms, and is one of the primary criteria used by most shoulder surgeons to assess the need for surgical intervention.
How to Differentiate Between Shoulder Joint Inflammation and Shoulder Tendon Tears
Differentiating between the two is crucial because the treatment path differs radically: joint inflammation is treated conservatively in most stages, while a complete tendon tear necessitates an early surgical decision to avoid retraction and fatty muscular degeneration.
| Differentiating Criterion | Shoulder Joint Inflammation | Shoulder Tendon Tear |
| Onset of symptoms | Gradual over months or years | Sudden after exertion or an accident |
| Type of pain | Deep, heavy, chronic | Sharp or burning, sometimes with a “popping” sound |
| Passive range of motion | Limited in frozen shoulder — relatively normal in other types of inflammation | Relatively preserved if the tear is partial |
| Muscle weakness | Relatively mild | Very prominent, especially when lifting the arm forward (Empty Can test) |
| X-rays | Joint space narrowing, cartilage wear, bone spurs | Normal or upward migration of the humeral head toward the acromion |
| MRI | Cartilage deterioration, synovial effusions, bone spurs | Partial or complete tendon tear with or without retraction |
| Most affected age group | Over 60 years | 40–60 years, often with a history of occupational or athletic activity |
Diagnostic Tests: X-rays vs. MRI
Magnetic Resonance Imaging (MRI) is the gold standard for diagnosing shoulder disorders, with an 88% accuracy in detecting tendon tears and 95% in detecting cartilage disorders, which is much higher than physical examination alone.
Three-view X-rays (True AP + Axillary + Supraspinatus outlet) are sufficient to evaluate osteoarthritis and measure joint space narrowing. A distance of less than 7 mm between the humeral head and the acromion indicates a large rotator cuff tear. Ultrasound is an available option at a lower cost in Cairo clinics and has good sensitivity for complete tears, but it depends on the operator’s experience.
Treatment of Shoulder Joint Inflammation
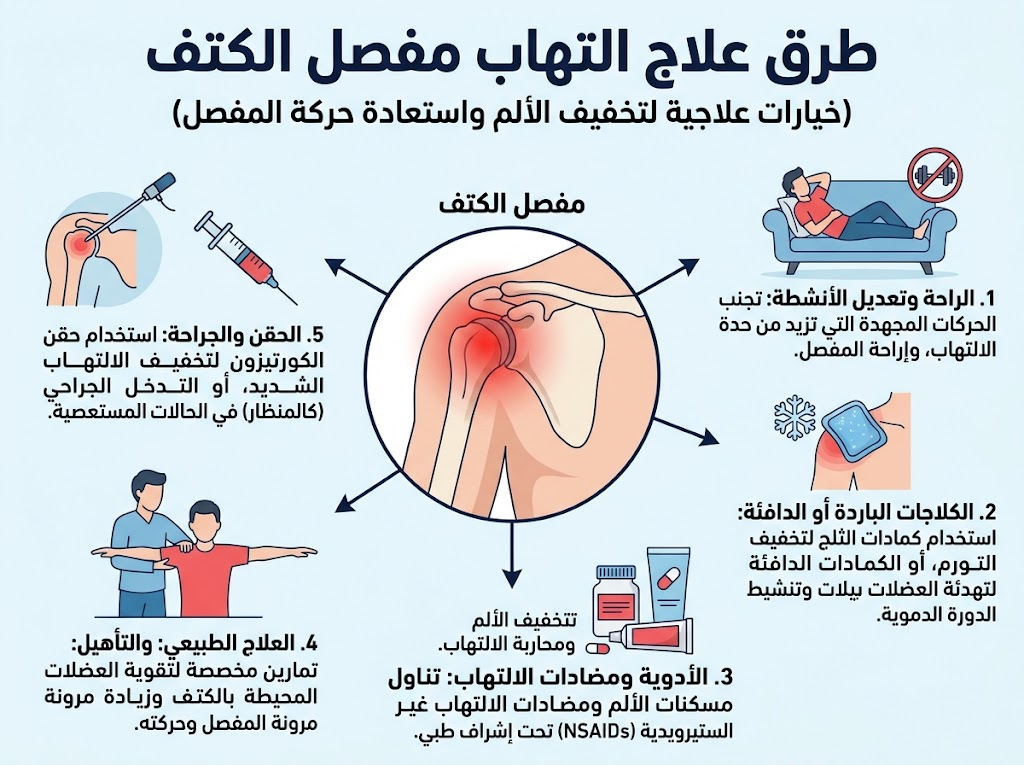
Conservative treatment is the first line in all degrees of shoulder joint inflammation unless there is a complete tendon tear or persistent failure of non-surgical treatment for at least 6 months.
Available Medications in Egypt
| Pharmacological Category | Scientific Name | Available Egyptian Brand Name | Usual Dosage | Note |
| NSAIDs | Diclofenac Sodium | Voltaren® / Cataflam® | 50 mg twice daily | Do not exceed 4 weeks without medical review |
| NSAIDs | Ibuprofen | Bravin® / Advil® | 400–600 mg 3 times | Taken with food |
| Cox-2 Inhibitor | Celecoxib | Celebrex® / Arthrox® | 200 mg daily | Safer for colon and stomach patients |
| Muscle Relaxant | Methocarbamol | Robaxasil® | 750 mg twice | Used for associated muscle spasms |
| Joint Supplement | Glucosamine + Chondroitin | Arthroflex® / Osteo Bi-Flex® | Per instructions | Benefit in the shoulder is less proven compared to the knee |
Cortisone injections inside the shoulder joint relieve pain with up to 70% effectiveness for 4–12 weeks; however, repeating them more than 3 times a year accelerates cartilage degradation.
| Injection Type | Substance | When Preferred | Approximate Duration of Effect |
| Cortisone | Triamcinolone / Methylprednisolone | Acute or moderate inflammation | 4–12 weeks |
| Hyaluronic Acid | Hyaluronic Acid (Synvisc® / Durolane®) | Moderate osteoarthritis — after cortisone failure | 3–6 months |
| PRP | Platelet-Rich Plasma | Resistant chronic tendinitis | 6–12 months |
PRP (Plasma) injections are available in a number of specialized medical centers in Cairo, with prices ranging between 3,500 – 7,500 Egyptian Pounds per session.
A structured physical therapy program for 8–12 weeks improves range of motion by 40–60% in non-surgical shoulder joint inflammation cases.
The program includes: passive and active range of motion exercises, strengthening of the rotator cuff muscles (tri-level exercises), and Ultrasound Therapy. Full compliance with sessions until the end of the program is essential to lock in results and prevent relapse, a common mistake among patients in Egypt who stop as soon as pain subsides.
When Does Shoulder Joint Inflammation Require Surgery?
Surgery is indicated upon failure of regular conservative treatment for 6 months with persistent pain limiting daily activity, or in the presence of a complete rotator cuff tendon tear, or advanced osteoarthritis confirmed by MRI and X-rays.
| Clinical Condition | Surgical Option | Documented Success Rate |
| Advanced osteoarthritis — intact tendons | Total Shoulder Arthroplasty | > 90% pain improvement |
| Osteoarthritis + complete rotator cuff tear | Reverse Shoulder Arthroplasty | 85–92% |
| Complete tendon tear without joint inflammation | Arthroscopic RC Repair | 90–95% |
| Resistant chronic bursitis | Arthroscopic Bursectomy | 80–85% |
| Resistant frozen shoulder (> 12 months without improvement) | Arthroscopic Capsular Release | 87–92% |
| Chronic AC joint inflammation | Mumford Procedure (Partial Clavicle Resection) | 85% |
Absolute or Relative Contraindications to Surgery: Active infection, severe neuro-muscular weakness due to axillary nerve damage, severe bone density loss preventing implant fixation, and patient refusal after full explanation of risks and alternatives.
Recovery Period After Major Surgeries (Shoulder Replacement): 3–6 months to return to daily activities, 9–12 months to return to work requiring lifting arms above head level.
Book Your Appointment with Prof. Dr. Ibrahim Abdelmonem
Prof. Dr. Ibrahim Abdelmonem, Professor of Orthopedic Surgery and Joints at Ain Shams University and Visiting Professor at Ohio State University, specializes in arthroscopic shoulder surgery and joint replacement. He welcomes patients at four locations in Cairo: Nasr City, Fifth Settlement, Mohandessin, and Batal Ahmed Abdel Aziz Street.

Frequently Asked Questions: Shoulder Joint Inflammation
What are the primary causes of shoulder joint inflammation?
What are the common clinical symptoms of an inflamed shoulder?
Why does shoulder inflammation typically worsen at night?
How is shoulder joint inflammation diagnosed clinically?
What non-surgical (conservative) treatments are available?
When are therapeutic injections indicated for shoulder inflammation?
What is the role of physical therapy in recovery?
When does shoulder inflammation require arthroscopic surgery?
How long is the typical recovery period after shoulder treatment?
What lifestyle modifications help prevent recurrent shoulder inflammation?
references
- Risk Factors for Rotator Cuff Tendinopathy: Systematic Review and Meta-Analysis — Journal of Rehabilitation Medicine (2019)
- Current and Future Advances in Tendinopathies of the Shoulder (Causes, Risk Factors & Management) — Rheumatology Advances in Practice (2023)
- Shoulder Tendonitis — Causes, Symptoms, Diagnosis & Treatment — Cleveland Clinic (2023)
- Supraspinatus Tendinopathy: Pathophysiology, Etiology & Conservative Treatment — Int J Sports Physical Therapy (2018)
- Occupational Risk Factors Associated with Soft Tissue Disorders of the Shoulder: A Literature Review — Ergonomics (CDC)
- Sport Activities and Risk of Shoulder Tendinitis in Construction Workers — BJSM
- Shoulder Tendonitis — Causes, Sports & Overuse — Apollo Hospitals Comprehensive Guide
- Systematic Review of Clinical Practice Guidelines on Diagnosis and Management of Shoulder Disorders — Arch Phys Med Rehabil (2024)
- Shoulder Tendinitis — Symptoms, Causes & Overview — Cleveland Clinic (2023)
- Shoulder Impingement Syndrome & Rotator Cuff Tendinopathy: Clinical Features, Signs & Symptoms — Core.ac.uk Review
- Current and Future Advances in Tendinopathies of the Shoulder (Symptoms, Diagnosis & Management) — Rheumatology Advances in Practice (2023)
- Systematic Review of Clinical Practice Guidelines on Diagnosis and Management of Shoulder Disorders — Arch Phys Med Rehabil (2024)
- Non-Surgical Treatments for Rotator Cuff Tendinopathy: A Narrative Review (2020–2025) — JFMK (2026)
- Rotator Cuff Tendinopathy: 2025 Clinical Practice Guideline — Physiotutors
- Corticosteroid Injection vs Physiotherapy for Rotator Cuff Tendinopathy: Systematic Review (2023)
- Comparison of Corticosteroid Injection, Physiotherapy and Combined Treatment for Chronic Subacromial Bursitis: RCT — PubMed (2023)
- Shoulder Rotator Cuff Disorders: Systematic Review of Clinical Practice Guidelines — Arch Phys Med Rehabil (2020)
- Platelet-Rich Plasma (PRP) for Rotator Cuff Tendinopathy: Systematic Review and Meta-Analysis — PLOS ONE (2021)