
The most common shoulder injuries in sports and daily life: rotator cuff tears, shoulder dislocation, ligament injuries — their causes, symptoms, and treatment. A medical guide by Prof. Dr. Ibrahim Abdelmonem, Orthopedic Surgeon.
Most Common Shoulder Injuries in Egypt and Sports
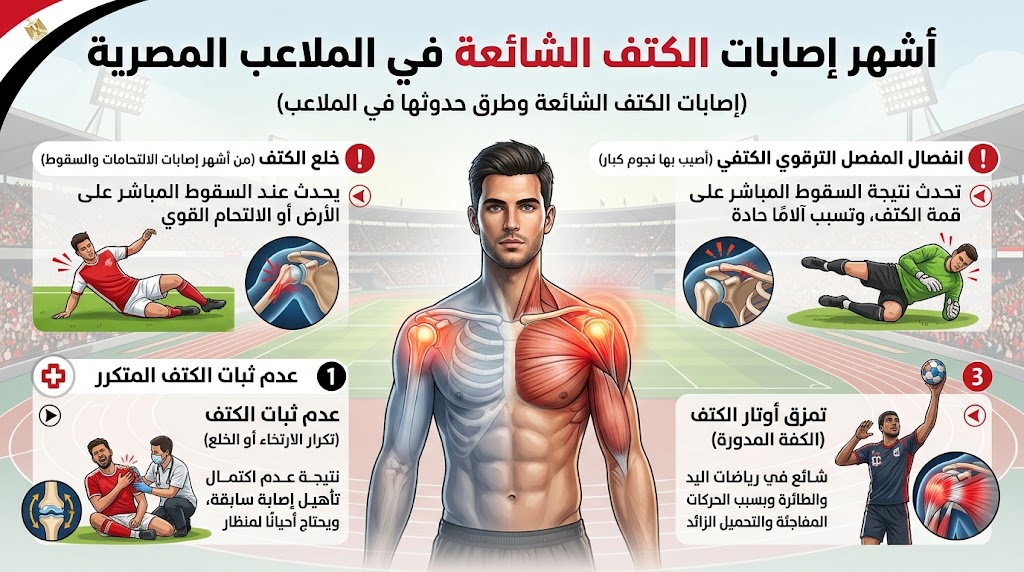
Shoulder injuries account for over 10% of total athletic injuries and rank first among soccer, basketball, and swimming injuries in Egypt. The shoulder is the most flexible joint in the body, and this exceptional flexibility is precisely what makes it most vulnerable to tears, dislocations, and ligament injuries.
| Injury Type | Most Affected Category | Incidence Rate Among Shoulder Injuries |
| Rotator cuff tendon tear | 40–60 years old, manual workers and athletes | Highest cumulative incidence with age |
| Anterior shoulder dislocation | Youth 15–35 years old, soccer players | 95% of dislocation cases |
| AC joint injury (Acromioclavicular ligament) | Young male athletes 20–35 years old | 9–10% of shoulder girdle injuries |
| Bruise and partial ligament tear | All categories, car accidents and falls | Most common in emergency centers |
| Proximal humeral fracture | Over 60 years old (osteoporosis) | Common after a fall on an outstretched arm |
Causes of Shoulder Injury
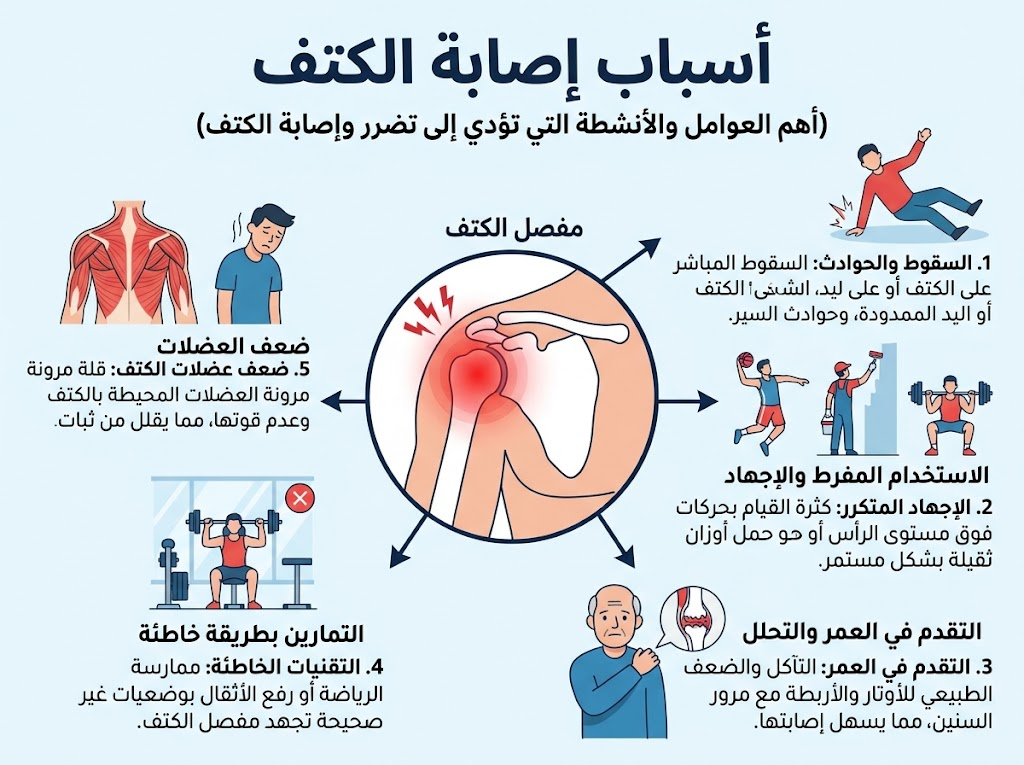
Shoulder injuries arise from two main mechanisms: direct trauma (a blow or fall) or cumulative repetitive stress that gradually weakens the tendons and ligaments without a single clear incident.
| Mechanism | Common Examples in Egypt | Most Probable Resulting Injury |
| Direct fall on the shoulder | Soccer pitches — motorcycle accidents | Shoulder dislocation or AC joint injury |
| Fall on an outstretched arm (FOOSH) | Falling from stairs or in factories | Proximal humeral fracture or AC injury |
| Sudden twist or strain | Heavy lifting — gym workouts | Rotator cuff tendon tear |
| Repetitive overhead movements | Workers, painters, volleyball players | Gradual inflammation and tear in the Supraspinatus |
| Direct physical collision | Soccer, volleyball, wrestling | Dislocation — ligament tear |
Factors Increasing Injury Risk: Intensive training without adequate warm-up, weakness of the rotator cuff muscles, a previous history of shoulder injuries, and age over 40 (tendons begin to lose their gradual flexibility).
Symptoms of Shoulder Injury by Type
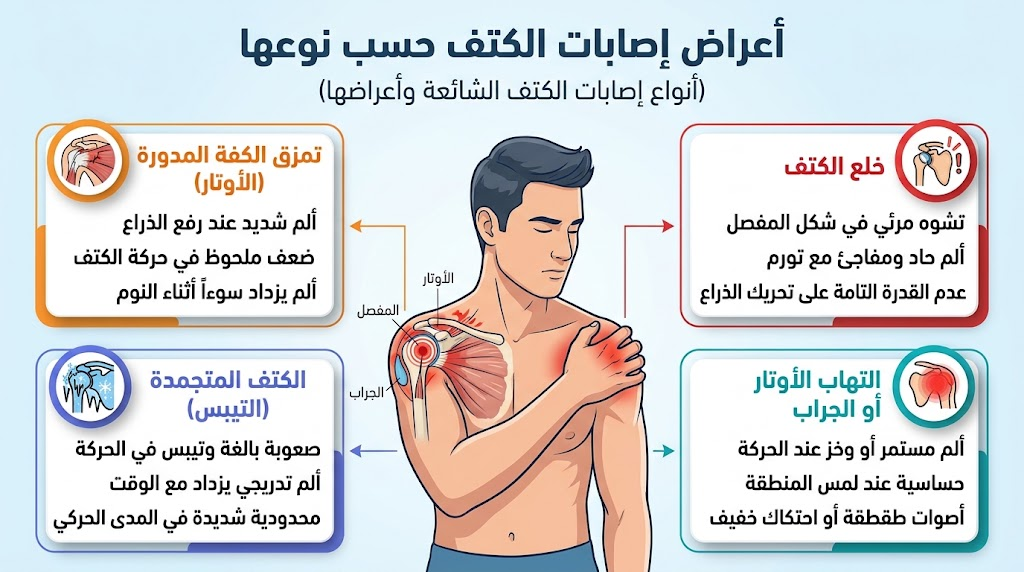
The most common mistake is assuming that every shoulder pain is a “simple bruise.” Each type of shoulder injury has a different symptom profile that determines diagnosis and guides treatment.
| Symptom | Potential Injury | Urgency Level |
| Immediate sharp pain with visible shoulder deformity | Shoulder dislocation or fracture | Immediate emergency |
| Sudden weakness in lifting the arm after exertion | Complete rotator cuff tear | Consultation within 48 hours |
| Bony lump above the shoulder (clavicle elevation) | AC Joint injury Grade 3 and above | Consultation within a week |
| Localized pain at the top of the shoulder radiating to the neck | AC Joint injury Grade 1–2 | Conservative treatment — non-urgent |
| Deep posterior pain worsening gradually with movement | Cumulative tendinitis | Regular consultation |
| Sensation that the shoulder “slips out and goes back” | Chronic instability after prior dislocation | Surgical evaluation |
Rotator Cuff Tendon Tears
A rotator cuff tear is a tear in one or more of the tendons of the muscle group that keeps the humeral head in place. One-third of tear cases require surgery; the remaining two-thirds improve with regular conservative treatment.
The four tendons making up the rotator cuff: Supraspinatus (responsible for lifting the arm — most commonly torn), Infraspinatus, Teres Minor (external rotation), and Subscapularis (internal rotation).
Tendon Tear Grades and Their Relationship to Surgical Decision
| Tear Grade | Definition | Accepted Treatment | Recovery Period |
| Partial < 50% tendon thickness | Tear does not fully penetrate the tendon | Conservative treatment: rest + physical therapy + injections | 6–12 weeks |
| Partial > 50% tendon thickness | Tear exceeds half the tendon thickness | 6 weeks conservative — surgery if no improvement | 3–4 months |
| Complete — small < 1 cm | Tendon is completely detached but without retraction | May heal conservatively in non-athletes | 3–6 months |
| Complete — medium 1–3 cm | Detachment with mild retraction | Arthroscopic surgery recommended | 4–6 months |
| Complete — massive > 5 cm | Detachment with retraction and fatty muscle degeneration | Arthroscopic repair or reverse shoulder replacement | 6–12 months |
Fatty muscle degeneration (Fatty Atrophy) — evaluated by the Goutallier classification on MRI — is the most influential factor in the surgical decision and its outcomes. Delaying treatment increases the degree of degeneration and reduces the chances of successful repair.
The success rate of arthroscopic rotator cuff repair ranges between 90–95% in specialized centers.
Shoulder Dislocation: Types and First Aid
Shoulder dislocation is the complete exit of the humeral head from the glenoid socket. 95% of dislocation cases are anterior, occurring mostly among young athletes after a fall or direct collision. The shoulder is the most frequently dislocated joint in the human body.
Symptoms of acute dislocation are unmistakable: severe immediate pain, obvious visible deformity in the shape of the shoulder, inability to move the arm, and numbness that may extend to the fingers if the axillary nerve is affected.
First Aid: Do not attempt to manually reset the shoulder yourself. Immobilize the arm with a temporary sling and head immediately to the emergency department. Resetting the joint in emergency centers is performed under painkillers and muscle relaxants; the non-surgical resetting success rate exceeds 98%.
Risk of Recurrence After First Dislocation: Reaches 80–90% in those under 20 years old. These patients are prime candidates for surgical intervention to repair the accompanying ligamentous tear (Bankart Lesion).

AC Joint Injury (Acromioclavicular Ligament) — Most Common on Egypt’s Pitches
AC joint injuries account for 9–10% of total shoulder girdle injuries and occur due to a direct fall on the shoulder or a side blow. They affect young male athletes at a 5:1 ratio compared to females.
Rockwood Classification — The Gold Standard for Assessing AC Injury Severity:
| Rockwood Type | Affected Ligament | Clavicle Elevation | Treatment Decision |
| Type I | Sprain in AC ligament — joint intact | None | Rest + painkillers only |
| Type II | AC ligament torn — CC ligament intact | < 25% | Conservative treatment 4–6 weeks |
| Type III | AC + CC ligaments torn | 25–100% | Conservative first; surgery if pain persists 3–6 weeks |
| Type IV–VI | Complete tear with posterior or severe clavicle displacement | > 100% | Surgical fixation — absolute necessity |
How to Treat Various Shoulder Injuries
Proper treatment of a shoulder injury begins with accurate diagnosis of the injury type and grade. Each treatment protocol differs, and misdiagnosis leads to incorrect treatment and deterioration of the condition.
Conservative Treatment and Available Medications in Egypt
| Protocol | Details | Duration |
| Relative rest + Ice | 20 minutes every two hours in the first 48–72 hours | First 3 days |
| Immobilization with brace or sling | Essential in shoulder dislocation and AC Type II–III injuries | 2–4 weeks depending on injury |
| Physical therapy | Range of motion exercises then gradual muscle strengthening | 6–12 weeks |
Medications:
| Category | Scientific Name | Egyptian Brand Name | Usual Dosage |
| NSAIDs | Diclofenac Sodium | Voltaren® / Cataflam® | 50 mg twice daily with food |
| NSAIDs – COX2 | Celecoxib | Celebrex® / Arthrox® | 200 mg daily — safer for the stomach |
| Muscle Relaxant | Methocarbamol | Robaxasil® | 750 mg twice — for associated spasms |
| Local Cortisone (injection) | Triamcinolone | Kenacort® | One injection inside the joint or bursa |
| PRP Plasma | Platelet-Rich Plasma | — | 3,500–7,000 EGP/session |
When is Surgery Necessary?
Surgery is a necessity — not an option — in four specific scenarios: a complete rotator cuff tendon tear with functional muscle weakness, recurrent shoulder dislocation with a documented Bankart tear, a Type IV–VI AC injury, and any injury with bone deformity or accompanying fracture.
| Injury | Surgical Procedure | Recovery Period |
| Complete rotator cuff tear | Arthroscopic RC Repair | 4–6 months |
| Recurrent shoulder dislocation + Bankart tear | Arthroscopic Bankart Repair | 4–6 months |
| AC Injury Type IV–VI | Surgical clavicular fixation (Weaver-Dunn / TightRope®) | 3–4 months |
| Proximal humeral fracture | Fixation or partial shoulder replacement | 4–8 months |
Book Your Appointment with Prof. Dr. Ibrahim Abdelmonem
Prof. Dr. Ibrahim Abdelmonem, Professor of Orthopedic Surgery and Joints at Ain Shams University and Visiting Professor at Ohio State University, specializes in arthroscopic shoulder and knee surgery, joint replacement, and bone tumors. He welcomes patients at four locations in Cairo: Nasr City, Fifth Settlement, Mohandessin, and Batal Ahmed Abdel Aziz Street.

Frequently Asked Questions: Common Shoulder Injuries
What is the difference between a simple shoulder bruise and a ligament or tendon tear?
What are the immediate first-aid steps when a shoulder injury occurs on the field?
How does an acromioclavicular (AC) joint separation happen in sports?
What is a labral tear (SLAP lesion) in athletes?
What imaging studies are required to accurately evaluate shoulder ligament and cartilage tears?
When does an acute shoulder dislocation require surgery rather than conservative care?
What is the difference between a glenohumeral dislocation and an AC joint separation?
What are the core phases of sports rehabilitation following shoulder ligament injuries?
What clinical and functional criteria determine a safe return to play for athletes?
How can athletes prevent recurrent shoulder injuries and tears?
references
- AAOS — Common Shoulder Injuries (OrthoInfo)
- AAOS — Appropriate Use Criteria for Rotator Cuff Injuries
- Orthopedic Reviews — AC Joint Separation: Rockwood Classification & Treatment
- Healthscope Orthopaedics — Common Shoulder Injuries Treatment Guide
- Shoulderdoc — AC Joint Classifications (Rockwood/Allman/Tossy)
- Common Shoulder Injuries — Types, Causes, Symptoms & Treatment Overview — Medical Research (2024)
- Systematic Review of Clinical Practice Guidelines on Diagnosis and Management of Various Shoulder Disorders — Arch Phys Med Rehabil (2024)
- Current and Future Advances in Tendinopathies of the Shoulder — Rheumatology Advances in Practice (2023)
- Prevalence of Rotator Cuff Tears: Systematic Review and Meta-Analysis — Frontiers in Physiology (2026)
- Surgical vs Non-Surgical Treatment for Full-Thickness Rotator Cuff Tears: Systematic Review — PMC
- A Systematic Summary of Systematic Reviews on the Rotator Cuff — Orthopaedic Journal of Sports Medicine (2018)
- Efficacy of Injections for Partial Rotator Cuff Tears: Systematic Review — PMC (2021)
- Shoulder Impingement Syndrome: Systematic Review — PMC (2016)
- Outcomes of Arthroscopic Surgery for Shoulder Impingement Syndrome: Systematic Review — Orthopedic Reviews (2025)
- Non-Surgical Treatments for Rotator Cuff Tendinopathy: Narrative Review — JFMK (2026)
- Corticosteroid Injection vs Physiotherapy for Rotator Cuff Tendinopathy: Systematic Review (2023)
- Risk Factors for Rotator Cuff Tendinopathy: Systematic Review and Meta-Analysis — J Rehabil Med (2019)